Mostrando entradas con la etiqueta ACUTE MEDICAL EMERGENCIES. Mostrar todas las entradas

miércoles, 7 de septiembre de 2016

SEPSIS

Sepsis is a serious illness. It happens when your body has an overwhelming immune response to a bacterial infection. The chemicals released into the blood to fight the infection trigger widespread inflammation. This leads to blood clots and leaky blood vessels. They cause poor blood flow, which deprives your body's organs of nutrients and oxygen. In severe cases, one or more organs fail. In the worst cases, blood pressure drops and the heart weakens, leading to septic shock (multisystem failure - shock).

  • Anyone can get sepsis, but the risk is higher in:
-people with weakened immune systems
-infants and children
-the elderly
-people with chronic illnesses, such as diabetes, AIDS, cancer, and kidney or liver disease
-people suffering from a severe burn or physical trauma

This response may be called systemic inflammatory response syndrome (SIRS).

Causes
The symptoms of sepsis are not caused by the germs themselves. Instead, chemicals the body releases cause the response.
A bacterial infection anywhere in the body may set off the response that leads to sepsis. Common places where an infection might start include the:
-bloodstream
-bones (common in children)
-bowel (usually seen with peritonitis)
-kidneys (upper urinary tract infection or pyelonephritis)
-lining of the brain (meningitis)
-liver or gallbladder
-ungs (bacterial pneumonia)
-skin (cellulitis)

For patients in the hospital, common sites of infection include intravenous lines, surgical wounds, surgical drains, and sites of skin breakdown, known as bedsores or pressure ulcers.

Symptoms
In sepsis, blood pressure drops, resulting in shock. Major organs and body systems, including the 
kidneys, liver, lungs, and central nervous system stop working properly because of poor blood flow.
A change in mental status and very fast breathing may be the earliest signs of sepsis.

In general, symptoms of sepsis can include: chills, confusion or delirium, fever or low body temperature (hypothermia), light-headedness due to low blood pressure, rapid heartbeat, shaking, skin rash and warm skin. Bruising or bleeding may also occur.

Fast action is key to prevent sepsis death:


Following the recommendations of The UK Sepsis Trust we can assess our patients easily. If our patient looks sick or the New Early Warning Score has triggered we should wonder if there is an infection present even if the source is not clear yet.

If there is an infection, we should look for ANY Red Flag Criteria:


If one of the above is present, the Sepsis 6 pathway should be started immediately. If none of the above is present we should look for any Amber Flag criteria:


If there is an Amber Flag criteria present a set of routine blood samples and an urgent senior review should take place within an hour, if Acute Kidney Injury is present the Sepsis 6 pathway should be started.

Sepsis 6 pathway
When the Sepsis 6 pathway has to be started, a treatment escalation plan should be made and the CPR status of the patient should be clarified. The patient has Red Flag Sepsis and all the following actions have to be completed within one hour:


If after delivering the Sepsis Six, the patient still has:
-systolic BP < 90 mmHg
-reduced level of consiousness despite resuscitation
-respiratory rate over 25 breaths per minute
-lactate not reducing
or the patient is clearly critically ill at any time, Critical Care Outreach team should be called immediately.


Sources:
-http://sepsistrust.org/
-https://medlineplus.gov/ency/article/000666.htm
-https://medlineplus.gov/news/fullstory_160574.html
-https://www.emaze.com/@AOZTZRZO/CAMPA%C3%91A-PARA-SOBREVIVIR-A-LA-SEPSIS.pptx

martes, 19 de mayo de 2015

SUDDEN COLLAPSE AND CARDIAC ARREST

Common causes of the sudden collapse:
-Cardiac: due to ventricular fibrillation or ventricular tachycardia in most cases, other causes can be severe bradycardia, asystole or pulmonary embolism.


-Respiratory: tension pneumothorax, aspiration/upper airway obstruction or massive haemoptysis.
-Gastrointestinal: catastrophic bleed (usually from oesophageal varices) or a ruptured abdominal aortic aneurysm.
-Anaphylaxis: a characteristic setting with a recognised trigger, wheeze, oropharyngeal swelling and severe hypotension.

Diagnosing cardiac arrest
There are four common scenarios:
1. pulseless and collapsed with ventricular fibrillation or ventricular tachycardia - cardiac arrest.
2. pulseless and collapsed with a flat trace - cardiac arrest.
3. pulseless and collapsed but with an electrical rythm (pulseless electrical activity or PEA) - cardiac arrest.
4. flat trace but patient looks well - has an electrode come off?.

THE CHAIN OF SURVIVAL
Basic life support (BLS)
Basic life support describes the process of:
-the initial assessment of the collapsed patient
-the techniques to keep the airway open
-the use of expired air ventilation and chest compression - CPR.

The primary helpers continue active resuscitation. Secondary helpers may need to fetch the crash trolley, make the medical and nursing notes available, ensure laboratory results are fed back to the arrest team, put any recent X-rays up on the viewing box, see to other patients in the ward and move any patient if appropiate and handle the relatives: phone calls and direct contact.

Sequence of actions:
1. Ensure safety of rescuer and patient
2. Shout for help. Check the patient and see if he responds.
3. If the patient responds: recovery position, check his condition (ABCDE), give oxygen, secure Iv access and attach monitors. Reassess regularly and handover to the Emergency Medical Team using a standarised communication framework (RSVP: Reason, Story, Vital signs and Plan of management).

If the patient does not respond: turn him on his back and open his airway by tilting his head and lifting his chin, remove any visible obstruction.
Keeping the airway open, look, listen and feel for normal breathing:
-if patient is breathing normally: turn him into recovery position and check for continued breathing.
-if patient is not breathing normally: check for signs of circulation and signs of life.

If there are signs of circulation, start rescue breathing, check for circulation every 10 breaths. If patient starts to breathe on his own  but remains unconscious, turn him into the recovery position.
If there are no signs of circulation or signs of life start chest compression, continuing compressions and breaths in a ratio of 30:2, at a rate of about 100-120 times a minute.
Continue resuscitation until the cardiac arrest team arrives to assist. Do not stop CPR to check the patient unless he starts to regain consciousness and shows clear signs of breathing normally again.

Advanced life support (ALS)
Once the arrest team arrives the situation can be reviewed, with the first priority being to analyse the heart rythm from the ECG monitor or via the self adhesive defibrillation pads.
In a cardiac arrest, the heart rhythm falls into one of two categories:
-Shockable rhythms: ventricular fibrillation and pulseless ventriculat tachycardia.
-Non-shockable rhythms: asystole and electrical complexes, but with no palpable pulse (PEA: pulseless electrical activity). This group needs emergency drugs (adrenaline) and continuing CPR.


Legally, the most senior doctor has the responsability of saying when to stop the resuscitation procedure.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

martes, 12 de mayo de 2015

MULTISYSTEM FAILURE - SHOCK

SHOCK

Classical features of shock:
-A systolic blood pressure of less than 90 mmHg
-Tachycardia
-An increased respiratory rate (>20 breaths/min) and reduced oxygen saturations
-Mottled, cool and clammy skin
-Evidence of hypovolaemia: dry mouth, dry axillary skin, postural hypotension, thirst.
-Low urine output (less than 0.5 ml/kg per h)
-Confusion or agitation progressing to coma.

Cardiogenic shock
In cardiogenic shock, the heart as a pump fails to propel blood around the circulation. The common causes are:
-heart muscle damage
-severe arrhythmia
-valve disease
-output obstruction


Hypovolaemic shock
In hypovolaemic shock, there is a reduction in the circulating blood volume due to either external fluid loss (upper gastrointestinal bleeding, severe diarrhoea and vomiting, DKA) or "internal loss" (acute pancreatitis, severe paralytic ileus).


Redistributive (low-resistance) shock
Redistributive shock is due to the effect of circulating toxins disturbing the normal distribution of blood flow within the body. Some vessels, notably those in the skin, open up and provide little or no resistance to blood flow.
Other vessels shut down in a pattern in which organs such as the kidney are starved of blood. In contrast to the other forms of shock, in redistributive shock the overall resistance to blood flow is reduced: the cardiac output is therefore high, the pulse is bounding and the peripheries are warm. The patient appears flushed and warm rather than grey and clammy. Without treatment, however, the progression is the same as that in other forms of shock - to kidney failure and to increasingly severe acidosis.
The main causes are sepsis (especially from gut and renal tract infections) and anaphylaxis.

ACUTE SEVERE HYPOTENSIVE COLLAPSE
Clinically, patients with shock present to the Acute Medical Unit as a problem of acute severe hypotensive collapse. Given this clinical situation, there are five groups of conditions to consider: cardiorespiratory collapse, massive pulmonary embolus, septicaemia, hypovolaemia and anaphylaxis.

Critical nursing tasks:
-Rapid assessment of the criticaly ill: ABCDE, maintain the safety of the patient.
-Recognition of a deteriorating patient:


-Measure the respiratory rate and the oxygen saturations.
-Measure the radial and apical pulse rates - monitor the heart.
-Measure the lying blood pressure and look for any postural decrease.
-Ensure large-bore venous access.
-Obtain an immediate 12-lead ECG.
-Assess the site and severity of any pain.
-Reassure the patient about the management plan and initiate symptom relief.
-Keep the relatives on the ward.


ANAPHYLACTIC SHOCK
Anaphylaxis is the term used for a severe generalised allergic reaction. The most common causes are foods (especially nuts), insect stings, drugs (especially antibiotics, aspirin and ACE inhibitors) and latex allergy.
From 5 min to an hour after exposure, the patient develops a generalised reaction with swellling, redness and itch. In cases of oral ingestion in food allergy, the swelling usually starts in the mouth and tongue progresses to upper airway obstruction. Occasionally, the delay from exposure to reaction is as long as 6h. 
The two potentially fatal complications are: airway obstruction and ciculatory collapse.


Emergency treatment:
-Intramuscular adrenaline (epinephrine).
-Oxygen.
-Fluids.
-Bronchodilators.
-Antihistamines.
-Steroids.
-Prevention: there must be effective education in allergen avoidance and good control of any underlying asthma by optimising the use of prophylactic anti-inflammatory treatment with inhaled steroids.

ACUTE KIDNEY INJURY (AKI)
The term Acute Kidney Injury applies to situations where there is a risk of acute renal failure and also to situations where renal failure is fully established. There are three stages in the deterioration from "at risk of" to "established" renal failure. They are defined by the urinary output:
1. Risk: urine output < 0.5ml/kg/hr for > 6 hours
2. Injury: urine output < 0.5ml/kg/hr for > 12 hours
3. Failure: urine output < 0.5ml/kg/hr for > 24 hours or anuric for 12 hours.


Nursing tasks in acute kidney injury:
-Prepare to start treatment for hyperkalaemia
-Carry out basic management of pulmonary oedema
-Identify sepsis: strong clues are fever, malaise, rigors and perhaps dysuria
-Identify hypovolaemia: symptoms of thirst and dizziness, signs of postural fall in blood pressure and low CVP (Central Venous Pressure)
-Confirm that the problem is not a simple outflow obstruction
-Take a full history
-Exclude rhabdomyolysis in prolonged immobility/coma
-Check the urine
-Ensure there is a system for reviewing the abnormal urea and electrolyte results on the ward.

Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

martes, 5 de mayo de 2015

ALCOHOL AND SUBSTANCE ABUSE

ALCOHOL ABUSE
-Acute alcohol intoxication: the main problems are hypoglycaemia, respiratory depression, airway protection and, in severe cases, fitting.
-Alcohol as a component of deliberate self-harm
-Alcohol dependence as a cause of deliberate self-harm
-Acute alcohol withdrawal syndromes: characterised by tremor, sweating, apprehension, nausea and vomiting, weakness and syncope, insomnia, auditory and visual hallucinations, fitting and severe confusion.
-Alcohol-induced disease: alcoholic gastritis, acute variceal bleeding, alcoholic liver disease or pancreatitis.
-Other alcohol-associated medical conditions: unexplained vomiting, atypical chest pain, binge-associated acute atrial fibrillation, hypertension, depression, unexplained falls and confusion in the elderly.

It is important to take a good drinking history to establish the amount and pattern of drinking and the level of dependence. 
The CAGE questionnaire:
-Have you felt you should Cut down?
-Have you been Annoyed by criticism of your drinking?
-Have you felt Guilty about your drinking?
-Do you ever have an Eye-opener in the morning to steady your nerves?
Two or more positive answers to the four questions suggests alcohol dependence.

Nursing tasks in alcohol withdrawal syndrome:
-Ensure patient´s safety.
-Check observations regularly and GCS.
-Monitor GMAWS.

-Observe for signs of trauma, nausea or pain.
-Look for signs of Wernicke´s encephalopathy : acute neuro-psychiatric reaction to severe thiamine deficiency common in alcohol misuse, characterised by acute onset of one or more of the following: acute confusional states, nystagmus and/or ataxia. It can progress to Korsakoff´s psychosis.
-Administer Pabrinex and Thiamine as prescribed, Librium (Chlordiazepoxide) should be prescribed as required.
-Provide a calm and reassuring environment as these patients are often frightened or apprehensive.


SUBSTANCE ABUSE

Cocaine
Cocaine imparts its desired effects by stimulating the release of the stress hormones (noradrenaline, adrenaline and dopamine) to inapppropriately high levels. The effects are dramatic, as may be the side-effects - notably stroke, heart attack and aortic dissection.


The nature of the cardiac damage includes cocaine-related chest pain, acute coronary syndrome, acute myocardial infarction, acute arrythmias and, with prolonged use, cocaine induced heart muscle damage. The sudden changes in pulse rate and blood pressure can trigger cerebral infarction, cerebral haemorrhage and can tear major blood vessels (aortic and coronary artery dissection).
Treatment of all of these complications should follow conventional lines except that beta-blockers are contra-indicated and that high-dose benzodiazepines may be needed to reduce cocaine-induced agitation.
  
Ecstasy
Ecstasy, or MDMA, has amphetamine-like properties which provide hyperstimulation, combined with the exertion of prolonged dancing, can result in:
-dehydration and electrolyte disturbance
-hyperarousal - agitation, tachycardia, hypertension
-muscle breakdown (rhabdomyolysis) and kidney failure
-hyperthermia up to 40°C
-convulsions
-acute liver failure
-severe acidosis

Management: reassurance and IV fluids are the main measures. Hyperthermia is managed by active cooling and with IV dantrolene 1mg/kg repeated as needed (maximum 10mg/kg). Acute agitation and convulsions respond to benzodiazepines. Acidosis may need correction with sodium bicarbonate.

Heroin abuse
Intravenous drug users are often admitted acutely with multiple complex medical, social and behavioural problems. There is frequently a conflict between the perception of the patient that withdrawal symptoms and pain are not being addressed and that of the carers who view challenging behaviour and "drug seeking". The key is an emphatic approach which is non-judgmental and focuses on the key issues of communication, co-operation and confidentiality (sometimes with the need to set defined limits to behaviour).
Heroin abuse is associated with several major health-related and psychosocial problems: HIV, hepatitis B and C, superficial and deep soft tissue sepsis, venous thromboembolic disease, opiate overdose, social isolation and crime.
Methods of heroin ingestion: inhaled (chase the dragon), smoked or injected (mainlining).


Heroin overdose
Patients are usually deeply comatose, with pin-point pupils. Treatment is with IV naloxone, the specific antidote, but reversal can be dramatic, leading to acute agitation, aggression and violence.

The current recommendations for a methadone treatment program are:
-only methadone syrup, not tablets, should be prescribed
-daily prescriptions should be given
-the effective maintenance dose should not exceed 50-100mg of methadone daily
Methadone programmes are carefully supervised and managed with a system of daily supply and directly observed ingestion. Apart from using methadone syrup, effective treatment programmes monitor drug ingestion with blood and urine testing.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

jueves, 30 de abril de 2015

DELIBERATE SELF-HARM AND OVERDOSES

DELIBERATE SELF-HARM
Vulnerable groups at risk of suicide:
-Recent acute psychiatric illness, particularly during the first week after discharge.
-Schizophrenia, especially in patients who are poorly compliant or lost to follow up.
-History of drug or alcohol abuse.
-Any patient who says that they are feeling suicidal, especially if accompanied by feelings of hopelessness.
-Patients living in social isolation with no family support.
-Several previous episodes of deliberate self-harm.
-A single episode of deliberate self-harm carries 1 in 20 rate of suicide within 10 years.


Type of patients admitted with deliberate self-harm:
-The embarrassed and impulsive: the spur of the moment, often triggered by a row and alcohol, not necessarily a trivial amount (often paracetamol) and low risk of recurrence or future suicide.
-The serious attempt: a planned event, carried out alone and in secret, no attempt to get help, suicide note, admits to the intended outcome, even "trivial" overdoses may represent a determined attempt at suicide.
-The recurrent attender: severe personality disorder, history of  violence, criminal convictions, drug and alcohol abuse, high risk of eventual success. 
-The high-risk self-harm: older, male, isolated, unemployed/retired, alcohol dependence, poor general health, violent method used, repeated attempts and suicide note.

Why do patients deliberately harm themselves?: to gain temporary respite, as a cry for help, as a signal of distress, communicating anger/eliciting guilt/influencing others and to end their lives.

Critical nursing tasks in deliberate self-harm:
-Care of the unconscious patient: ABCDE (check observations, GCS, ECG, gain venous access, etc).
-Take appropiate blood (glucose, alcohol, paracetamol, aspirin, LFT, INR) and urine tests (opiates, cocaine, amphetamines, ecstasy, hallucinogens).
-Decontamination of the gut: gastric lavage or activated charcoal (single dose or multiple doses).
-Ensure that all relevant information is available: mental state, past psychiatric history, previous self-harm, alcohol use, assessment of suicidal intent.
-Provide a suitable and safe environment in which to recover consciousness.


SPECIFIC OVERDOSES


  • Benzodiazepines

Benzodiazepines, unless taken as part of a more toxic cocktail, depress the consciousness level, but not sufficiently to put respiration at risk unless the patient also aspirates. Management is based on maintaining respiration and keeping a secure airway. The specific antagonist IV flumazenil reverses benzodiazepine coma immediately, but the drug has potential problems: the effects of a single dose soon wear off which may trigger acute agitation and if tricyclic antidepressants may also have been taken, flumazenil is contraindicated.


  • Paracetamol

Paracetamol remains the most common cause of acute liver failure in the UK.
For most patients 12g of paracetamol or more than 150mg per kg body weight can produce severe liver damage.

Clinical picture of severe paracetamol toxicity:
-0-24 h: minimal immediate symptoms, mild nausea and vomiting within a few hours, liver function tests normal in the first 12 h, abnormal by 18 h.
-24-48 h: right upper abdominal pain with continued vomiting, liver tenderness, progressively deranged liver function tests, prolonged prothrombin time, loin pain, haematuria, proteinuria and deteriorating kidney function.
-Days 3 and 4: maximum liver damage on fourth day, jaundice and increasing confusion with grade 3/4 hepatic encephalopathy.

Immediate management:
-Establish the exact timing of the overdose (time tablets swallowed, time help arrived, could the overdose have been staggered over several hours?).
-what else was taken?
-is this a susceptible patient (eating disorder, HIV, cystic fibrosis or malnourished, chronic alcoholic, epileptic/anti-TB drugs, underweight).
-consider activated charcoal: overdose taken within an hour and methionine is not going to be used (charcoal inactivates methionine).
-take blood for measurement of. paracetamol levels.
-start N-acetylcysteine (Parvolex) treatment if indicated (patient needs to be weighed for the correct dose). Repeat LFT´s and prothrombin time at the end of the infusion (20 h).

There is a poor prognosis 24 h after the overdose, patients should be discharged only after psychosocial assessment, after completion of N-acetylcysteine and if there are no symptoms.
Clear instructions should be given to the patient who discharges themself: to return if there is abdominal pain, persistent vomiting or confusion.


  • Antidepressants

There are two types of antidepressants used in deliberate self-harm:
-the older tricyclic antisepressants: these are dangerous and cause coma, convulsions and cardiac arrhythmias. Dothiepin is the most dangerous.
-the new generation of antidepressants (SSRIs). drugs like fluoxitine can cause "serotonin syndrome" - acute confusion, fever, muscular rigidity and twitching.
Management:
-The main dangers are: respiratory depression, cardiac arrythmias and convulsions.
-Patient remains at risk for at least 12 h after admission and are prone to arrythmias if they mobilise prematurely.
-Treatment: gastric lavage or single-dose activated charcoal.


  • Carbon monoxide poisoning

Carbon monoxide is odourless, colourless and extremely dangerous. Patients suffer hypoxic damage to the heart and central nervous system.
This gas has two important sources: incomplete combustion of carboniferous domestic fuel associated with faulty installations or accidental fires and car exhaust fumes.
Clinical picture:
-Acute exposure: headache, nausea and dizziness progressing to collapse and loss of consciousness. In severe poisonng with coma, there may be skin blistering and pressure-induced muscle damage. The limbs are spastic and there may be acute heart damage, pulmonary oedema or increased intracraneal pressure.
-Subacute exposure: slower onset of nausea, vomiting, headaches and drowsiness. The clinical picture can mimic flu or gastroenteritis - a source of confusion. As with gastroenteritis, a whole household can be affected if exposed to the same source.

Assessment and management:
-ABCDE
-Give immediate high-concentration oxygen
-Consider hyperbaric oxygen, especially in cases of pregnancy, COHb > 20% or signs of neurological dysfunction
-If it is accidental domestic exposure, the local environmental health department should be involved to assess the safety of the house.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

miércoles, 22 de abril de 2015

THROMBOEMBOLIC DISEASE

THROMBOSIS AND THROMBOEMBOLISATION
Thrombosis refers to the process in which a mass of clot forms inside an artery or vein. It consists of a dense network of fibrin in which are trapped variable portions of red cells and platelets.
Thrombosis blocks the vessel and impairs blood flow.
Arterial thrombosis leads to ischaemic tissue damage (myocardial infarction, stroke and peripheral vascular disease), whereas in venous thrombosis the consequences are due to back pressure and local swelling (oedema).

If the clot disintegrates, parts of it can break off, producing emboli that travel onwards: in venous thrombosis through the veins to the lungs (pulmonary embolus), and in arterial thrombosis through the arteries to major organs such as the brain (cerebral embolus), limbs (peripheral embolus), kidneys (renal infarction) and intestine (acute bowel ischaemia).

Superficial thrombophlebitis
Thrombophlebitis is a painful inflammation of the superficial veins. Classically it is seen with infected venous cannulae, but it also commonly occurs in patients with varicose veins.


The clinical picture is of palpable and very tender cords of thrombosed and inflamed veins, with the overlying skin appearing reddened or bruised.
Thrombophlebitis is not in itself dangerous, but may accompany deep vein thrombosis.
Management is removing the cause and treating the symptoms.

Deep vein thrombosis (DVT)
Deep vein thrombosis is a more serious problem, because of the risk of fatal pulmonary embolus. Most DVTs start in the deep veins of the calf, termed the distal veins, where they cause local pain and swelling. One in five extend up the leg to involve the proximal veins in the thigh and pelvis (popliteal and iliofemoral thrombosis). The risk of a pulmonary embolus from a proximal vein thrombosis is very high. A significant proportion of the survivors will develop a postphlebitic syndrome in the affected leg, with chronic swelling, varicose veins, skin pigmentation, recurrent thrombosis and venous ulceration.

The management is based on preventing progression of the thrombotic process by using heparin for an immediate effect, followed by warfarin in the medium to long term. The aim of treatment is to stabilise the situation, prevent extension, reduce the chances of embolisation and lower the risk of recurrence.

Critical nursing tasks in suspected DVT
-Give the first dose of heparin immediately.
-Ensure there is adequate pain relief.
-Be vigilant for acute ischaemia.
-Care of the pressure areas.
-Reassure the patient.
-Document all current regular and intermittent medication.
-Document the target INR (usually 2.5).
-Ensure a warfarin loading schedule is followed by the prescribing doctors.

*Other causes of a swollen painful leg: cellulitis or necrotising fasciitis.

Pulmonary thromboembolism
Most pulmonary emboli arise from the proximal veins in the thigh and pelvis. Depending on their size, emboli that travel to the lung either become wedged in the main pulmonary arteries, where they block the outflow of blood from the right side of the heart, or pass onwards to become trapped in the lung peripheries.

-The former, termed massive pulmonary emboli, produce a disastrous decrease in cardiac output, leading to sudden death or acute hypotensive collapse. Massive pulmonary emboli can move or start to break up either naturally or during the course of cardiopulmonary resuscitation. Thrombolytic drugs can help to dissolve the embolus and are used in the unstable hypotensive patient. Heparin will prevent further emboli, and as most patients who survive the first embolus die from a recurrence within the first few hours, it is important to start treatment urgently. Warfarin is added for long-term prevention.

-The smaller emboli in the periphery of the lungs produce wedge-shaped areas of lung damage and give rise to overlying pleurisy. The management of smaller peripheral emboli is based on preventing further and possibly bigger emboli by giving heparin and, subsequently, warfarin.


Classic features of a pulmonary embolus:
-Pleuritic chest pain
-Breathlessness
-Respiratory rate > 20 breaths/min
-Haemoptysis

Critical nursing tasks in acute pulmonary embolus:
-ABCDE: immediate resuscitation.
-Ensure adequate oxygenation.
-Provide an adequate circulation.
-Relieve the patient´s symptoms.
-Assess the response to treatment.
-Anticipate the need for urgent heparin therapy or thrombolysis.
-Prepare the patient for further procedures.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

jueves, 16 de abril de 2015

DIABETIC COMPLICATIONS

ACUTE MEDICAL CONDITIONS ASSOCIATED WITH DIABETES

  • Diabetic renal disease: one-third of Type I and between one-quarter and one-half of Type II diabetic patients develop diabetic kidney disease (diabetic nephropathy).

Urinary protein loss is often the first indication of renal disease.  An early sign that diabetes is affecting the kidneys is the presence of "micro" albuminuria - a loss of 30-300 mg per 24 hours - which can be detected using a specialised screening test.
-Proteinuria indicates probable renal involvement.
-Proteinuria goes hand-in-hand with cardiovascular complications and diabetic eye disease.
-Proteinuria is strongly associated with hypertension.
-Switching off the renin-angiotensin-aldosterone system with ACE inhibitors or angiotensin II receptor blockade slows down the deterioration from microalbuminuria to advanced diabetic nephropathy.
Important tasks if diabetic renal disease is discovered: careful blood pressure control, treatment with ACE inhibitors and related drugs, tight diabetic control, correction of lipids and advice on cessation of smoking.

  • Diabetic neuropathy: diabetic nerve damage is very common - it occurs in around one-third of patients with type II diabetes. There are two types of diabetic neuropathy:
-Peripheral neuropathy: it gives problems on the feet (numbness, poor skin nutrition and impaired mobility). The patient has no warning of trauma to the feet, nerve damage and muscle imbalance lead to foot deformity and pressure damage over abnormal bony prominences. Elsewhere in the body, nerve damage can lead to neuralgia with severe, recurrent and often undiagnosed pain in the thighs and abdomen.
-Autonomic neuropathy: it leads to abnormal regulation of involuntary muscle activity, notably in the bladder (painless retention, overflow and recurrent urinary infection), in the control of the blood pressure (severe postural hypotension) and in gastric emptying (regurgitation and aspiration of the stomach contents).


  • Cardiovascular disease: the main manifestations of cardiovascular disease are angina, myocardial infarction and heart failure. 
  • Cerebrovascular disease: the vascular damage in diabetes affects both the larger cerebral vessels and the cerebral microcirculation. Diabetic cerebrovascular disease presents with typical stroke-like symptoms due to thrombosis or hypertension-related cerebral haemorrhage. It should be assumed that any change in the consciousness level of a diabetic patient has a metabolic cause until proved otherwise. 
  • Peripheral vascular disease: it presents as an emergency with ischaemic problems in the limbs due either to acute arterial occlusion or to vascular complications in the feet: ulceration, infection and gangrene.


*The DIGAMI  regimen: an example of controlling the blood sugar in acute illness. Click here.


MANAGEMENT OF ACUTE DIABETIC EMERGENCIES

DKA (Diabetic Ketoacidosis)
Causes: infection, disruption of insulin treatment, new-onset diabetes, etc.

Underlying mechanism: in DKA there is an acute shortage of insulin. As a result, the liver produces and releases excessive amounts of glucose that appear in the blood and in the urine. The heavy glucose load in the urine pulls in water and electrolytes by osmosis, leading to losses of fluid, potassium, sodium, phosphate and magnesium. Because there is shortage of insulin, sugar cannot enter the cells  and so the body starts to burn adipose tissue as an alternative energy source. The adipose tissue breaks down to free fatty acids, which are converted into ketones by the liver. Ketones are acidic substances, so when excess ketones appear in the blood they produce an acidosis.
  
Management: adequate insulin replacement and correction of fluid and electrolyte loss.

Critical nursing tasks in DKA:             
-Observations: oxygen saturation, blood sugar, blood pressure, pulse (ECG), temperature and respiratory rate.
-Glasgow Coma Score.
-Test for urinary ketones.
-Examine for signs of infection.
-Ensure that the initial infusions are correctly prescribed and administered.
-Monitor patient´s progress and address his/her physical needs.
-Provide reassurance and support, initiate plans to prevent this from happening again.


Hyperosmolar Non-Ketonic Diabetic Coma (HONK)
This relatively rare complication is seen in the elderly Type II diabetic patients, the patient presents extremely unwell, with very high blood sugars and impaired consciousness levels, but without ketoacidosis. They are usually profoundly dehydrated due to osmotic fluid loss. The history usually involves a precipitating illness.
The diagnosis is made from the clinical setting and the finding of a high blood osmolality.
Management: CVP monitoring, nasogastric intubation to prevent aspiration and judicious fluid therapy. 
As the sodium levels are usually very high, hypotonic saline (0.45%) can be used in place of the initial isotonic saline.
Because the blood is so concentrated, the patients are at great risk of thrombosis and should be anticoagulated.


Hypoglycaemia.
Symptoms: click here .
Management:
-If the patient is conscious and cooperative: 100ml Lucozade, 6 glucose tablets or four teaspoonfuls of sugar.
-If there is an impaired consciousness level: intravenous glucose or intramuscular glucagon.


Infective complications in diabetes: the acute diabetic foot.
The severily infected foot that brings the diabetic patient in as an emergency will characteristically have cellulitis spreading from an area of ulceration. By the time the patient needs admission, the ulcer will have become infected and the whole foot may be at risk.


Signs of worsening and spreading infection:
-The foot becomes increasingly painful and tender.
-The patient looks ill.
-The skin goes purple and red or black blisters appear.
-There is an increase in: pulse, temperature, blood sugars, white cell count or respiration rate.
-The infection spreads into the leg.

Management:
-control the diabetes
-treat infection
-provide adequate pain relief
-salvage the limb if there is critical ischaemia (by-pass or angioplasty)
-prevent the worsening of any pressure damage.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

jueves, 9 de abril de 2015

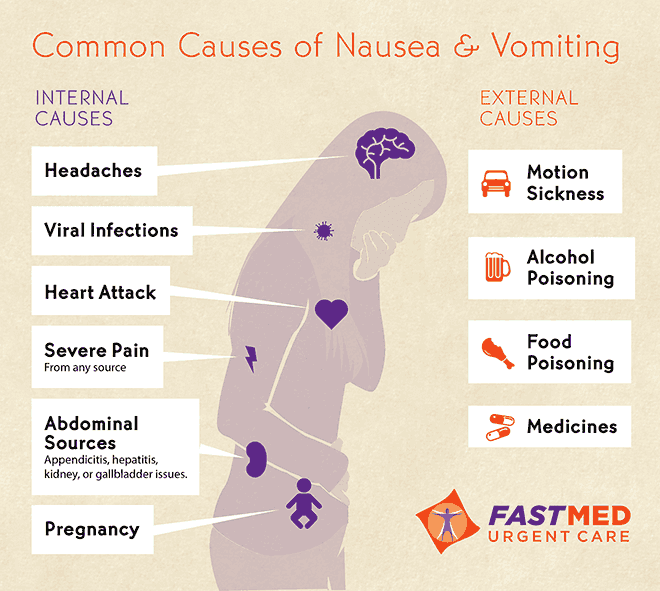
Nausea, vomiting and acute gastrointestinal events

NAUSEA AND VOMITING
Consider the underlying mechanisms and potential causes: 
-establish the history (when and how did it start, other symptoms or illnesses, pain, has it happened before, anyone else got the same symptoms?).
-is this gastrointestinal disease (any diarrhoea, abdominal pain, obstruction, is the cause acute liver damage, alcohol abuse?)
-is it drug-related? (any new medication, digoxin toxicity or opiate side-effect?)
-could this be raised intracranial pressure? (headache, malignant disease or altered consciousness level?)
-could this be metabolic? (renal failure, sodium and calcium levels, ketoacidosis?).

Nausea and vomiting in acute medical conditions:
-Migraine: commonly accompanied by vomiting. Other causes of headache like meningitis, increased intracranial pressure and subarachnoid haemorrhage are also associated with vomiting.
-Myocardial infarction: vomiting is an important feature that distinguishes the pain of a myocardial infarction from that of angina and is often accompanied by nausea and sweating.
-Sepsis: vomiting can be the only symptom of hidden infection, particularly in infections in the kidneys and lower urinary tract.
-Acute gastric dilatation: gross gastric distension leads to upper abdominal swelling associated with nausea, often accompanied by hiccups and belching. A common outcome is sudden vomiting, aspiration an cardiac arrest.


ACUTE UPPER GASTROINTESTINAL HAEMORRHAGE

Causes:
-Helicobacter pylori infection and bleeding peptic ulcers
-Acute gastritis, duodenitis and acute erosions (stress ulcers)
-Mallory-Weiss tear:
-Oesophageal varices
-Gastric and oesophageal cancer
-Dieulafoy´s erosion: erosion of a congenitally abnormal artery in the lining of the stomach, emergecy surgery is often required.

Management:
-Ensuring the safety of the patient: ABCDE.
-Investigations: endoscopy.
-Assessing the degree of bleeding: history (presence of melaena with haematemesis, clots in the vomit and recognisable blood in the stool, bleeding accompanied by syncope, postural dizziness and overwhelming thirst suggest a major bleed) and examination (pale and clammy, tachycardia of more than 100 beats/min , systolic blood pressure of less than 100mmHg and postural hypotension).
-Risk assessment with the Rockall Score:


Important nursing tasks: 
-ensure the safety of the patient, assess the likely severity of the initial blood loss and report any further loss, save any important evidence (vomited blood, fresh melaena), report any abdominal pain.
-correct the oxygen saturation,
-secure the venous access and ensure accurate fluid balance charts,
-complete baseline observations, measure the pulse, blood pressure and respiratory rate. Report any changes on vital signs which should be checked at appropiate intervals.
-identify the signs of shock (pallor, sweating, restlessness, confusion),
-take an appropiate history, ask about liver disease and clotting disorders,
-reassure the patient and attend to patient´s basic comforts, warn about the likely need for an endoscopy.

ACUTE LIVER FAILURE AND HEPATIC ENCEPHALOPATHY
Acute liver failure can be precipitated by an acute event such as viral hepatitis or by a background of chronic liver disease with portal hypertension.

Components of acute liver failure:
-impairment of the consciousness level: the combination of poor liver function and portosystemic shunting means that toxic substances are either dealt with ineffectively by the liver or bypass it altogether. The result is a toxic encephalopathy with imapirment of the consciousness level that can progress rapidly from confusion and agitation to deep coma. It is useful to assess and follow changes using the Hepatic encephalopathy scoring system:


-bleeding varices and clotting abnormalities: patients in acute liver failure are at great risk from upper gastrointestinal bleeding due to the combination of varices and impaired clotting.
-sepsis: infection can trigger or complicate acute liver failure.
-metabolic abnormalities: the main problems are hypoglycaemia and renal failure.

Critical nursing tasks in acute liver failure:
-Ensure the safety of the patient: ABCDE.
-Gain venous access.
-Carry out top-to-toe examination.
-Liaise with patient´s family.
-Ascertain the possible causes of acute liver failure: the most common are paracetamol poisoning and acute hepatitis.
-Explain the likely interventions in the first 48 h: endoscopy, radiology, transfusions, multiple infusion lines and possible transfers.
-Obtain a drug history.

Other important nursing tasks are: determine accurate fluid balance, identify sepsis, reassure the patient and manage confusion and disorientation, carry out general nursing measures.

ACUTE ABDOMINAL PAIN
Abdominal pain is a common complaint on the acute medical ward and it is a feature of several medical conditions.

Nursing tasks:
-Establish the site and pattern of the pain.
-Assess the severity of the pain.
-Look for signs of shock (tachycardia, hypotension and increased respiratory rate).
-Examine for abdominal rigidity and peritonitis: the most obvious features of acute peritonitis are localised pain on coughing and board-like abdominal rigidity, the patient does not want to move, appears shocked and is usually vomiting. Acute peritonitis may be accompanied by signs of sepsis (hypotension, rapid thready pulse and cold, mottled extremities).
-Prepare for resuscitation: the basic requirements are oxygen, IV fluids, nasogastric intubation and urinary catheterisation.

Also, it is important to look at associated clinical features, prepare the patient for further investigations, review the previous history, the urine test results and the stool chart.


ACUTE DIARRHOEA

Infective diarrhoea:


Assessment:
-History of recent foreign travel
-Ask about other possible cases
-Have there been recent doubtful meals/mass catering...?)
-History of recent antibiotic therapy
-Is this patient at special risk?: elderly, diabetic, immunosuppressed, cardiac and kidney disease.
-Is there a history of recurrent diarrhoea?: inflammatory bowel disease.

Nursing assessment: ABCDE, assess fluid loss, look for evidence of shock and diagnosis from stool cultures.

Nursing management: 
-Infection control.
-Correct fluid deficit and keep up with the loss of fluid in the stool and vomit (fluid balance and stool chart).
-Antibiotics are rarely needed unless there are signs of complications: persistent fever with a failure to improve, development of severe colitis or shock, signs of infection, severe colitis with the risk of haemorrhage, toxic dilatation and perforation or HUS (Haemolytic Uraemic Syndrome).

Clostridium Difficile diarrhoea
The indiscriminate use of antibiotics has led to a large rise in bowel infections due to clostridium difficile. The clinical picture varies from mild diarrhoea to severe colitis with fever, systemic sepsis and death.


Diagnosis relies on two fresh stool specimens from any patient with mushy or liquid stools beng sent urgently to the labwith a request for the C.difficile toxin. The result should be available on the same day. Specific treatment is with oral metronidazole or vancomycin.

The following indicate a potentially severe infection:
-Temperature > 38.5
-More than 7 episodes of diarrhoea per 24 hours
-Pulse > 100
-WCC > 15 x 109
-A 50% rise in initial creatinine level (developing renal failure)
-Distended abdomen and no diarrhoea.

C. difficile and its spores contaminate and survive on surfaces such as commodes and bedside equipment and, in a busy ward , are easily spread by staff from one patient to another.

Enteric precautions: a single room with an en-suite commode, staff wearing gloves and apron who wash their hands with soap and water before entering and leaving the room, liquid soap and disposable wipes for the patient.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011

miércoles, 1 de abril de 2015

ACUTE NEUROLOGICAL PROBLEMS

INITIAL MANAGEMENT

-GCS and ABCDE: Assessing and keeping the patient alive:
Ensuring adequate ventilation and maintaining the circulation are the immediate priorities in any patient.

  • Glasgow Coma Scale


As  a general rule the scores reflect the severity of the neurological status:
-13 to 15: mild
-9 to 12: moderate
-3 to 8: severe
Coma is defined as a GCS of less than 9.
  • Critical nursing observations: blood sugar, pupillary responses, temperature, pulse, blood pressure, respiratory rate, oxygen saturations, GCS, top to toe examination and a reliable history.

Broadly there are two types of coma: medical coma, which is due to conditions such as liver failure, respiratory failure and diabetic ketoacidosis, in which the management is primarily aimed at the underlying disease; and neurological coma due to conditions such as stroke, subarachnoid haemorrhage and meningitis.

Causes of coma
  • Cerebral hemisphere malfunction:
-drug and alcohol intoxication
-hypoxic brain damage
-stroke
-metabolic disorders
-infection
-post-tonic-clonic convulsion
  • Brain stem damage:
-direct damage (brain stem stroke)
-indirect damage (cerebral mass or oedema)

STROKE AND STROKE-LIKE EMERGENCIES

Stroke is a syndrome of rapidly developing clinical signs of focal or global disturbance of function, with symptoms lasting 24 hours or longer with no apparent cause other than of vascular origin.


Causes:
  • Cerebral infarction (cerebral embolus or thrombosis):
-Anterior circulation infarcts: which result in a variable combination of one-sided weakness (hemiparesis), one-sided sensory loss (hemianaesthesia), visual disturbance (gaze paralysis) and partial loss of the visual field. In addition, there is a variable disturbance of higher functions such as language, neglect of the affected side and incontinence.
*TACI (total anterior circulation infarct), PACI (partial anterior circulation infarct) and LACI (Lacunar anterior circulation infart).

-Posterior circulation infarcts (POCI): also termed a brain stem CVA. Symptoms affect both sides of the body and also, affect coordination in talking, swallowing, looking and balancing. These patients have combination of dysarthria (slurred speech), dysphagia (difficulty swallowing), double vision and dizziness. 


  • Transient ischaemic attacks (TIA): these are minor strokes caused by the passage of small emboli that negotiate the cerebral circulation without producing any permanent damage.

  • Intracerebral haemorrhage                          

  • Subarachnoid haemorrhage

  • Subdural haemorrhage

  • Extradural haemorrhage

Nursing the patient with a stroke: the first 24h.
-Avoiding aspiration pneumonia and assessing the swallow. Assess security of the airway and maintain oxygen saturation.
-Monitor pulse, temperature and blood pressure.
-Medical history.
-Managing urinary incontinence which suggests disordered higher cortical function and is common in anterior circulation strokes. Catheterisation causes infection and reduction of the bladder capacity so it chould be avoided.
-Communication: vision, hearing, speech and language must be evaluated and documented at an early stage so it will be possible to spot and monitor any changes.

Interventions in the first 24h
-Diagnosis: FAST (Facial drop, Arm weakness and Slurred speech Test)


The Rosier Scale shown above is used to differentiate stroke from "look-alikes" including hypoglycaemia, syncope and epilepsy.
-Imaging: head CT scan.
-Acute drug intervention.
-Monitor blood pressure, temperature and blood sugar.
-Cerebral oedema may develop after a severe stroke and produce a deterioration in the consciousness levelwithin the first day or so.
-Reversing warfarin.
-Avoiding pressure sores: click here for more information.
-Resuscitation status.
-Avoiding venous thromboembolism. stroke victims are at risk of VTE, DVT and pulmonary embolus. 


MENINGOCOCCAL MENINGITIS
Meningococcal bacteria normally live quite naturally in the oropharynx of about 10% of the healthy population. In meningococcal disease , for some unexplained reasonthe bacteria become virulent and invade the bloodstream . The result is meningicoccal septicaemia and, if the nervous system is also invaded, meningococcal meningitis.

Clinical features of meningococcal infection:
-fever
-haemorrhagic rash
-altered level of consciousness
Septicaemia: influenza, vomiting, muscle pain and drowsiness.
Meningitis: photophobia, headache, neck stiffness and coma.


Clinical deterioration can be extremely rapid, the causes of death in meningitis are septicaemic shock and increased Intracranial Pressure (ICP).


Nursing tasks
-Assessment of ABCDE and vital signs every half an hour. Including fluid balance.
-ECG monitoring.
-Give oxygen and secure IV access.
-Administer immediate IV antibiotics (ceftriaxone or cefotaxime).
-Measurement of GCS.
-Note any rash.
-Discuss isolation for 24 hours with Control of Infection.
Other important nursing tasks are: 
-detain any relatives for further history and advice on contacts,
-ensure there are no drug allergies and ensure immediate specimens are taken for bacteriology (blood cultures, urgent PCR, clotted sample for meningococcal serology and oral or nasal posterior pharyngeal wall swab. Also, preparations should be made for a lumbar puncture if needed to confirm diagnosis. 

The signs of worsening meningitis:
-rapidly progressing rash
-poor peripheral circulation: capillary refill > 4 seconds, systolic blood pressure < 90mmHg and falling urinary output
-respiratory rate < 8 or > 30 breaths/min
-pulse < 40 or > 140 beats/min
-falling (less than 12) or fluctuating (by more than 2) GCS
-development of a focal limb weakness
-fitting
-falling pulse and climbing blood pressure.


SUDDEN LOSS OF CONSCIOUSNESS: FAINTS AND FITS
Sudden loss of consciousness followed by a recovery is usually due to a faint (syncope) or a fit (tonic-clonic convulsion). The history will differentiate fits and faints in most cases, as well as knowing the triggers, onset, the attack and the recovery details.

SYNCOPE
Syncope is due to a sudden reduction in the blood supply to the brain, in most cases, if the patient stays horizontal there is a full and rapid recovery. If the patient is upright, the blood supply does not return rapidly and the syncope may progress to an anoxic convulsion (convulsive syncope).
The reduction in cerebral blood supply has two possible causes:
-sudden change in heart rate (heart block, ventricular tachycardia)
-sudden change in blood pressure (reflex syncope, acute gastrointestinal haemorrhage, acute pulmonary embolus, drug side effect).

Types of syncopes
-Cardiac syncope
-Reflex syncope
-Situational syncope

EPILEPTIC SEIZURES
Click here for a detailed explanation.

Nusing tasks:

  • Patients who have regained consciousness:
-primary assessment ABCDE
-measure blood sugar and sitting/standing blood pressure
-12-lead ECG and cardiac monitor/telemetry for arrhythmias
-look for injuries, painful areas, bruising and swelling especially in wrists, ankles, hips and shoulders
-look for signs of upper gastrointestinal blood loss (coffee-ground vomit or melaena)
-look for signs of DVT
-obtain drug history and detain relatives or witnesses for more information.
  • Patients who are fitting:
-primary assessment ABCDE (especially airway and good venous access)
-ensure the patient cannot injure himself and place him in the recovery position
-give high concentration oxygen with a non re-breathing mask at 15L/min
-carry out blood sugar measurement and bloods for drug levels, biochemistry, clotting, etc.
-take a full history, especially concerning drugs and alcohol.


  • Patients with status epilepticus: status epilepticus is defined as fits that continue for 30 min or more without intervening periods of recovery and is a medical emergency. The management is the same as for a single fit but there is a risk of drug-induced respiratory depression. Close monitoring is needed and if the patient´s conculsions cannot be stopped within an hour, the patient needs ITU care.


ACUTE PARALYSIS OF THE LOWER LIMBS

Possible causes:
-spinal cord disorders: acute diseases of the spinal cord are compressive (urgent surgery), inflammatory (specific drug therapy) or vascular. Urgent MRI will differentiate between the three groups.
-Guillain-Barré syndrome: is an ascending paralysis that starts in the feet and moves progressively up the body, to an extent that the respiratory muscles are often involved. The disease can progress rapidly over a matter of hours and put the patient´s breathing at risk.
Respiratory monitoring is the key for the management of the syndrome.


Source:
-A nurse´s survival guide to acute medical emergencies, R. Harrison and L. Daly, Elsevier 2011